
Last Updated on October 9, 2026
Healthcare organizations use several standard code sets when billing payers. CPT and HCPCS codes describe procedures and supplies. ICD-10 codes define diagnoses and patient conditions. Revenue codes are different. They identify the department or type of service provided in a facility setting.
Even though revenue codes may not explain a clinical service on their own, they shape how the claim is interpreted on the payer’s end. They are required on institutional claims submitted through the UB-04 (CMS-1450) form and serve as a bridge between the clinical service and the location or department where the patient received care.
When used correctly, revenue codes create clarity in the billing record. When applied incorrectly or left blank, they can delay payment or trigger preventable denials even when the CPT or HCPCS codes are accurate.
The Benchmarks High-Performing Hospitals Achieve in 2026
Table of Contents
- What Is a Revenue Code in Medical Billing?
- Where Revenue Codes Appear on the UB-04
- Revenue Codes vs. CPT and HCPCS Codes
- How Revenue Codes and CPT/HCPCS Codes Work Together
- Where Revenue Code Errors Occur
- How the Chargemaster Controls Revenue Code Assignment
- Revenue Code Validation Before Claim Submission
- Where Revenue Integrity Begins on the Claim
- FAQs
What Is a Revenue Code in Medical Billing?
A revenue code is a four-digit numeric code used on institutional claims to identify the accommodation, department, or category of facility service associated with a charge line.
Revenue codes are used in facility billing, not professional billing. Hospitals, skilled nursing facilities, hospices, inpatient rehabilitation facilities, and mental health facilities use them when billing payers. They appear on the UB-04 claim form, the standard form for institutional providers.
Every revenue code belongs to a standardized list maintained by the National Uniform Billing Committee (NUBC). The codes range from 0001 to 9999.
Common examples include:
- 0450 – Emergency Room
- 0360 – Operating Room Services
- 0250 – Pharmacy
- 0121 – Inpatient Room and Board (Private Room)
The purpose of the revenue code is to tell the payer which department delivered the service. This helps the payer verify that the billed services match the clinical documentation and the procedure codes submitted on the same claim.
Where Revenue Codes Appear on the UB-04
The CMS-1450, commonly referred to as the UB-04, is the institutional paper claim form used by hospitals and other qualifying institutional providers. Its electronic counterpart is the 837I.
Revenue codes are reported in:
Revenue codes identify the accommodation or ancillary service associated with each institutional charge line. CMS instructs providers to report the appropriate revenue code in FL 42 alongside the corresponding charge information.
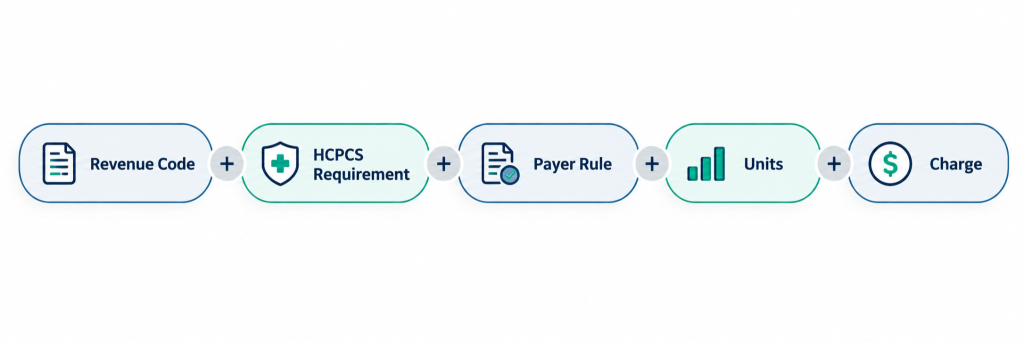
A facility claim line may therefore contain several connected data elements:
Revenue Code → CPT/HCPCS where applicable → Units → Charge
If one component does not align with the others, the payer may not interpret the line as intended.
For readers comparing institutional and professional claim structures, our CMS-1500 Medical Billing Guide explains how professional claims differ from the UB-04 environment.
Common Revenue Code Categories
Revenue codes are grouped into recognizable categories. Knowing the major groups makes it easier to review claims and catch mapping errors.
| Revenue Code | Service Category | Typical Use |
|---|---|---|
| 0110 |
Private room, general
|
Private inpatient room and board |
| 0121 |
Inpatient Room and Board Room (Private)
|
Two-bed inpatient accommodation |
| 0250 |
Pharmacy, general
|
General pharmacy services |
| 0300 |
Laboratory, general
|
General laboratory services |
| 0360 |
Operating room, general
|
Operating room services |
| 0450 |
Emergency room, general
|
Emergency department services |
| 0490 |
Ambulatory surgical care
|
General ambulatory surgery |
| 0636 |
Drugs requiring detailed coding
|
Drugs requiring specific identification |
| 0710 |
Recovery room, general
|
Post-procedure recovery services |
| 0762 |
Observation room
|
Observation services |
Recognizing these categories helps billing teams validate whether the revenue code, CPT/HCPCS code, units, and charge describe the same facility service.
Revenue Codes vs. CPT and HCPCS Codes
Revenue codes and CPT/HCPCS codes may appear together on the same institutional claim line, but they serve different purposes.
| Code Type | What It Communicates | Example |
|---|---|---|
| Revenue Code |
Facility department, accommodation, or service category
|
0360 Operating Room |
| CPT/HCPCS |
Procedure, service, supply, drug, or item
|
Procedure-specific CPT/HCPCS |
| ICD-10-CM |
Diagnosis or reason for care
|
Patient-specific diagnosis |
| ICD-10-PCS |
Qualifying inpatient facility procedure
|
Inpatient procedure code |
For a deeper explanation of how procedure and diagnosis coding differ, see our article on Working With ICD-10 and CPT Code Sets.
Example: Operating Room Claim Line
Consider a patient undergoing a surgical procedure in a hospital. The facility claim may include:
- Revenue code 0360 → identifies the operating room service category
- Applicable CPT/HCPCS code → identifies the procedure or service where required
- Units and charge → represent the facility resources being billed
The revenue code does not replace the CPT/HCPCS code. It provides additional facility-level context to the claim.
Are Facility Claim Lines Mapping Correctly?
AnnexMed helps hospitals review revenue-code mapping, procedure-code alignment, and institutional claim accuracy before billing issues move downstream.
Review Your Hospital Billing WorkflowHow Revenue Codes and CPT/HCPCS Codes Work Together
Not every revenue code follows the same HCPCS reporting requirement.
NUBC guidance distinguishes revenue codes according to the HCPCS indicator associated with the code:
- Y: the provider should report the appropriate HCPCS code
- N: a HCPCS code should not be required
- Blank: the payer may establish an applicable HCPCS reporting requirement
NUBC also permits providers to report HCPCS information in certain situations where the indicator is blank or “N,” subject to billing circumstances.
This makes revenue-code validation more than a simple one-to-one crosswalk.
Billing teams need to consider:
For example, a payer may expect detailed drug identification with a specific revenue category, while another facility charge may not require an accompanying HCPCS code at all.
Where Revenue Code Errors Occur
Revenue-code errors frequently begin upstream of claim submission.
For a deeper look at payer-specific billing differences, see our article on Managing Multi-Payer Hospital Billing Challenges.
When these issues have already become payer denials, Denial Management Services can help trace the failure back to the underlying coding, charge, or claim-line issue.
How the Chargemaster Controls Revenue Code Assignment
Revenue-code accuracy often begins inside the hospital Charge Description Master (CDM) rather than at final claim submission.
The basic path looks like:
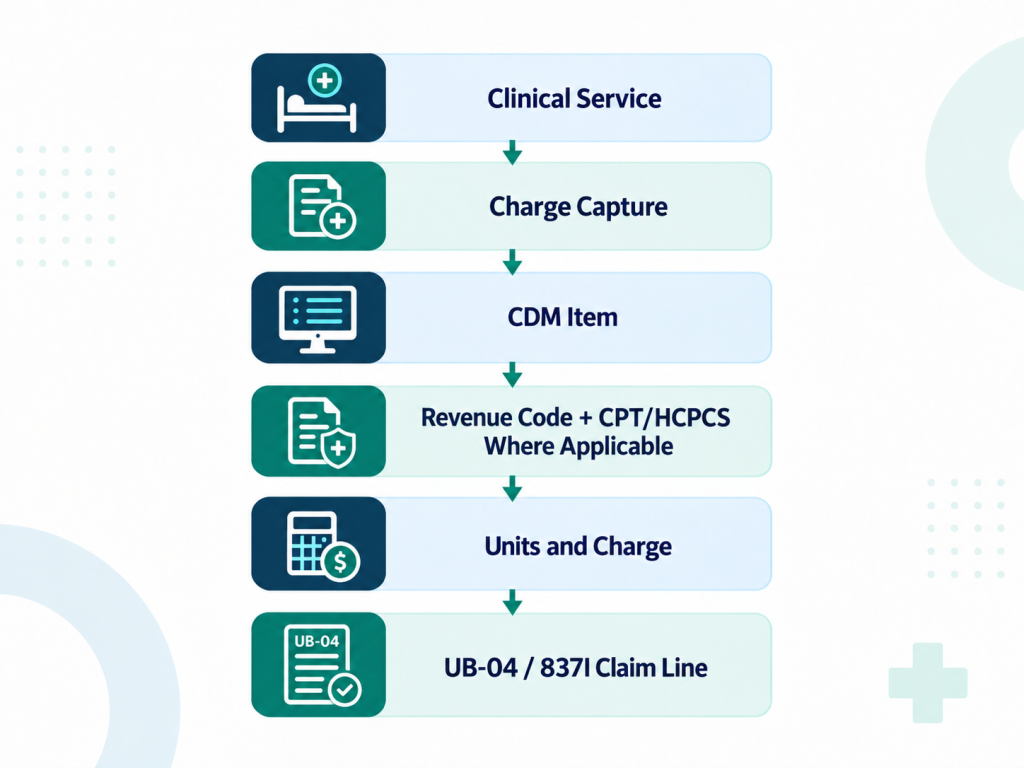
The chargemaster may contain the service description, department, CPT/HCPCS code, revenue code, units, pricing, and other billing logic needed to turn clinical activity into a facility charge.
When that mapping becomes outdated, even consistently documented services can generate consistently inaccurate claims.
AnnexMed observation: Revenue-code errors that appear repeatedly across different patients may indicate a chargemaster or charge-capture problem rather than an isolated coder error.
Revenue Code Validation Before Claim Submission
Before an institutional claim is released, billing teams should confirm:
- Revenue code reflects the correct facility service category
- CPT/HCPCS is present when required
- Revenue code and CPT/HCPCS combination is supported
- Units match the service or item billed
- Charges align with current CDM configuration
- Payer-specific reporting requirements have been checked
- No conflicting code or charge combinations remain
- Current NUBC and payer guidance is being used
This review is particularly important when new services, drugs, departments, or payer rules are introduced because an incorrect mapping can quickly become a repeatable claim issue.
Where Revenue Integrity Begins on the Claim
Revenue codes may occupy only one field on an institutional claim, but the accuracy of that field depends on several upstream processes working together.
A service must first be captured correctly, mapped through the appropriate chargemaster logic, paired with CPT/HCPCS information where required, assigned accurate units and charges, and validated against payer requirements before the claim reaches adjudication.
AnnexMed helps hospitals connect these points across charge capture, coding validation, claim review, denial prevention, and reimbursement follow-up, so recurring revenue-code problems can be traced back to the process or configuration creating them.
The value is not simply correcting one UB-04 claim. It is strengthening the path that turns documented clinical activity into an accurate, defensible facility charge.
Strengthen Revenue Integrity From Charge to Claim
AnnexMed helps hospitals connect coding, charge validation, claim review, denial prevention, and reimbursement follow-up across institutional billing workflows.
Talk to a Hospital Billing ExpertFAQs
A revenue code is a four-digit code used on institutional claims to categorize the accommodation, department, or type of facility service associated with a charge.
Revenue codes are reported in Form Locator 42 of the UB-04/CMS-1450. They identify the facility accommodation or ancillary service associated with the corresponding charge line.
No. Revenue codes categorize the facility service or charge type, while CPT and HCPCS codes identify specific procedures, services, items, drugs, or supplies where applicable.
No. NUBC revenue-code guidance includes HCPCS indicators showing when HCPCS should be reported, should not be required, or may depend on payer requirements.
Hospitals can improve accuracy by maintaining current chargemaster mappings, validating CPT/HCPCS relationships, reviewing units and charges, monitoring payer rules, and analyzing recurring claim edits or denials for upstream mapping problems.


