

Last Updated on October 1, 2026
Pediatric CPT coding is not simply about selecting a code. A single encounter may include a well-child visit, developmental screening, immunizations, evaluation of an acute concern, or telehealth follow-up, each with its own coding, documentation, and payer requirements.
Accurate pediatric billing depends on translating what happened during the encounter into the right preventive, E/M, vaccine administration, screening, newborn, critical-care, and modifier reporting pathway. When those elements do not align, claims may deny, downcode, or leave reimbursement on the table.
This guide covers commonly used pediatric CPT codes, documentation requirements, modifiers, telehealth considerations, ICD-10 specificity, common billing errors, and practical workflows that can help practices submit cleaner claims and reduce preventable revenue leakage in 2026.
Table of Contents
- Preventive and Sick Visits
- Pediatric CPT Code Quick Reference
- Immunization CPT Codes
- CPT Codes for Pediatric Screenings
- Newborn and Critical Care Codes
- Important Modifiers in Pediatric Coding
- Telehealth Billing Considerations
- ICD-10 Specificity in Pediatric Billing
- Common Pediatric Billing Errors
- Pediatric Coding Cheatsheet
- Building a Cleaner Pediatric Claim Workflow
- Smarter Pediatric Billing Starts With the Right Partner
- FAQs
Preventive and Sick Visits
Preventive CPT codes 99381–99395 apply to age-based preventive medicine services for new and established patients. These visits are not generic physicals. They include age-appropriate history, examination, anticipatory guidance, counseling, and risk-factor assessment.
Problem-oriented office or outpatient E/M services generally use 99202–99215. Code selection is based on medical decision-making or total time, as applicable.
Both service types may be reported on the same date when the problem-oriented E/M service is significant and separately identifiable from the preventive visit.
Accurate pediatric billing depends on ensuring the documentation, code selection, and claim submission remain aligned. Explore more about pediatric billing services designed around preventive, acute, and developmental pediatric encounters.
Example: Well Visit With Ear Pain
A child presents for a scheduled well visit and also reports ear pain.
- 99391 may apply to the preventive service.
- 99213-25 may apply when the provider separately evaluates and treats acute otitis media.
- The record should include a distinct assessment and plan for the acute condition.
A short statement such as, “In addition to preventive services, evaluated and treated acute otitis media,” helps establish that the E/M work was separate from routine preventive care.
AnnexMed observation: Modifier 25 denials in pediatric billing often start with documentation, not code selection. When the acute assessment and plan are not clearly separate from preventive services, billing teams may need to reconstruct the visit only after a denial occurs.
When denials become recurring rather than isolated, the focus needs to shift from claim-level correction to root-cause analysis and prevention. AnnexMed’s Denial Management services connect denial resolution with root-cause insights and prevention workflows.
Pediatric CPT Code Quick Reference
The following table provides a practical reference to commonly discussed pediatric CPT code categories in this guide. Code applicability, documentation requirements, bundling rules, and payer coverage should be validated against current CPT guidance and payer-specific policies before implementation.
| Service Category | Common CPT Codes | Key Documentation Consideration |
|---|---|---|
|
Preventive medicine
|
99381 – 99395 | Age, patient status, preventive services, and required documentation |
|
Office/outpatient E/M
|
99202–99215 | Medical decision-making or applicable time |
|
Developmental screening
|
96110 | Standardized tool, result, interpretation, and follow-up |
|
Behavioral assessment
|
96127 | Assessment tool, result, and clinical documentation |
|
Vision screening
|
99173 | Screening method and result |
|
Hearing screening
|
92551 | Screening method and result |
|
Vaccine administration
|
90460–90474 | Vaccine administration details and applicable counseling requirements |
|
Newborn care
|
99460–99465 | Setting, timing, provider role, and services documented |
|
Pediatric critical care
|
99471–99476 | Critical-care services, setting, age, and applicable reporting requirements |
Immunization CPT Codes
Vaccine billing requires two reporting elements: the vaccine product code and the administration code. Missing either can result in incomplete reimbursement.
For patients through age 18, when face-to-face counseling is provided by a physician or other qualified healthcare professional, report:
- 90460: First component of each vaccine or toxoid product administered.
- 90461: Each additional component of the same vaccine or toxoid product.
A component is an antigen that targets a particular disease. For example, DTaP contains components for diphtheria, tetanus, and pertussis. When counseling requirements are met, report one unit of 90460 for the first component and two units of 90461 for the additional components.
When counseling is not provided, or when the patient is age 19 or older, vaccine administration may be reported from the 90471–90474 series, based on the route of administration and the number of vaccines given.
Example: Multiple Vaccines at One Visit
A 2-year-old receives:
- MMR: 3 components
- DTaP: 3 components
- Hepatitis A: 1 component
When the counseling requirements are met, this encounter may include:
- 90460 × 3: One first component for each vaccine product.
- 90461 × 4: Two additional components for MMR and two additional components for DTaP.
Product Codes (e.g., 90707 for MMR, 90700 for DTaP, 90633 for Hep A) must still be reported in addition to the administration codes.
The note should document the vaccine products administered, counseling provided, relevant risks and benefits discussed, and applicable Vaccine Information Statement requirements.
CPT includes standalone immunization counseling codes for qualifying counseling provided when no vaccine is administered that day. Confirm payer adoption, code requirements, and documentation standards before adding these codes to your workflow.
AnnexMed observation: Vaccine underpayments are often cumulative. A missed 90461 unit may look small on one claim, but repeated component-counting errors throughout a busy immunization schedule can create meaningful reimbursement leakage.
Capture More From Every Pediatric Claim
From accurate coding and timely claim submission to denial management and AR follow-up, AnnexMed helps pediatric practices address revenue leakage and strengthen their financial performance.
Explore Our Pediatric Billing ServicesCPT Codes for Pediatric Screenings
Screenings are routine in pediatric preventive care, but payer payment depends on the supporting documentation. For every screening, the record should identify the standardized tool or method, score or result, clinical interpretation, and follow-up plan.
Developmental and Behavioral Screenings
- 96110: Standardized developmental screening, such as ASQ or PEDS.
- 96127: Brief emotional or behavioral assessment, such as PHQ-9 or GAD-7.
For example: “ASQ-3 completed; communication domain below cutoff; speech therapy referral placed.”
A statement such as “screened, normal” may not provide enough support for the billed service.
Vision and Hearing Screenings
- 99173: Quantitative visual acuity screening, such as Snellen-chart testing.
- 92551: Pure-tone hearing screening.
- 92587 / 92588: Otoacoustic emissions testing.
- 92567: Tympanometry when middle-ear assessment is clinically indicated.
Document the method, result, and plan. For example, Vision screen 20/30 OU; recheck at next annual preventive visit.
Coverage for instrument-based vision screening, otoacoustic emissions, and other advanced screening services can vary by payer. Verifying benefits before the visit can reduce preventable rework; AnnexMed’s eligibility and benefit verification services can help teams confirm coverage requirements before services are delivered.
Newborn and Critical Care Codes
Office-based pediatric coding is only part of the revenue cycle. Newborn, NICU, and PICU services involve setting-specific code families, daily reporting rules, and more complex bundling considerations.
Newborn Care Codes
- 99460: Initial hospital or birthing-center care for a normal newborn, per day.
- 99461: Initial care for a normal newborn outside a hospital.
- 99462: Subsequent hospital care for a normal newborn.
- 99464: Attendance at delivery.
- 99465: Newborn resuscitation at delivery.
Code selection depends on the care setting, timing, provider role, and clinical services documented.
Neonatal and Pediatric Critical Care
- 99468–99469: Initial and subsequent neonatal critical care, reported per day for critically ill infants younger than 28 days.
- 99471–99472: Initial and subsequent pediatric critical care, reported per day.
- 99475–99476: Subsequent pediatric intensive care.
Many routine services performed as part of critical care may be included in the daily critical-care service. Before separately reporting a service, review the CPT code descriptor, NCCI edits, documentation, and payer-specific guidance. Services that are truly distinct and separately identifiable may still be reportable with appropriate modifiers when supported.
For high-value NICU and PICU claims, a medical coding audit can help identify recurring modifier, documentation, and bundling issues before they result in denials or underpayments.
Scale Your Pediatric Practice With Clean Claims
With AnnexMed’s coding experts, your practice can expand services confidently, knowing billing accuracy and cash flow are protected.
Talk to our Coding ExpertImportant Modifiers in Pediatric Coding
Modifiers can materially affect pediatric claim adjudication. The most common high-risk modifiers include 25, 59, and 63.
| Modifier | Typical Pediatric Use | Documentation Requirement |
|---|---|---|
| 25 |
Separate problem-oriented E/M service on the same date as a
preventive service or procedure
|
Distinct assessment, medical decision-making, and treatment plan |
| 59 |
Distinct procedural service when no more specific modifier applies
|
Support for separate site, session, lesion, encounter or procedure |
| 63 |
Qualifying surgical procedure performed on an infant weighing
less than 4kg
|
Exact infant weight on the date of service, verify CPT eligibility and exclusions |
Modifier 59 should not be used simply to override a payer edit. It is appropriate only when documentation supports a genuinely distinct service.
Telehealth Billing Considerations
Pediatric telehealth billing in 2026 remains payer-specific. Before submitting a claim, verify the eligible service, covered modality, patient location, place of service, required modifier, and documentation requirements.
Some payers may allow qualifying office or outpatient E/M services for telehealth encounters, while others use dedicated telehealth code families. Modifier 95, audio-only reporting, and POS 02 or POS 10 rules should be verified against the payer’s current policy rather than applied universally.
Document:
- Whether the visit was audio-video or audio-only.
- Who participated, such as the child, parent, guardian, or caregiver.
- The provider’s location and patient location when required.
- Total time or medical decision-making, as applicable.
- Consent or other payer-required telehealth documentation.
A payer-specific telehealth reference guide can help prevent denials caused by incorrect modifiers, place-of-service codes, or unsupported modalities.
ICD-10 Specificity in Pediatric Billing
Accurate CPT coding is only one part of a clean pediatric claim. ICD-10-CM codes must reflect the condition, symptom, screening purpose, or preventive-service context documented in the medical record.
For FY 2026, pediatric practices should pay close attention to:
- Laterality: Right, left, bilateral, upper, or lower anatomical specificity where available.
- Congenital conditions: Use the most specific documented syndrome or congenital diagnosis.
- Disease status: Distinguish active disease, history, follow-up, and remission status when applicable.
- Symptom detail: Document precise symptom location, duration, severity, and associated findings.
- Screening versus diagnosis: Use appropriate screening diagnoses when no condition is identified, and update diagnosis reporting when a condition is found or treated.
Before annual ICD-10-CM updates take effect, update EMR templates, payer edits, superbills, and coding references. Confirm new-code mapping through official ICD-10-CM files and payer guidance before implementing new workflows.
For organizations managing high coding volumes, periodic coding audits can help identify recurring specificity, sequencing, modifier, and documentation issues before they translate into denials or reimbursement gaps.
Common Pediatric Billing Errors
Most pediatric billing errors are not isolated mistakes. They often originate in incomplete templates, missing charge-capture controls, or inconsistent documentation habits.
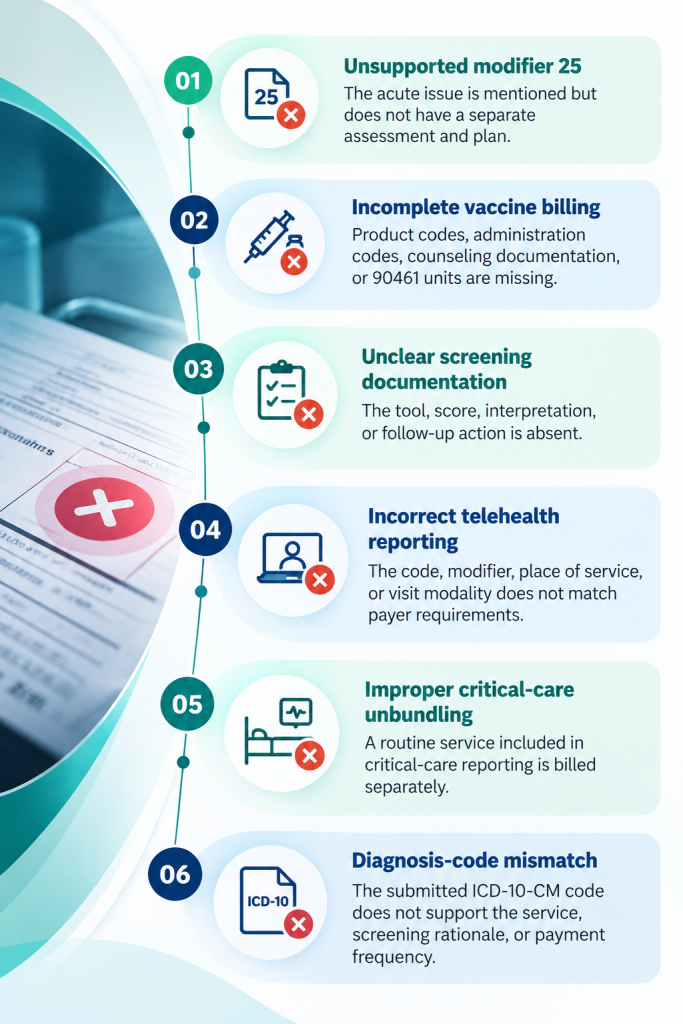
These errors may appear as individual claim issues, but recurring patterns can point to broader revenue-cycle gaps. Documentation, coding, charge capture, payer requirements, and denial trends should be reviewed together to understand where revenue leakage is originating.
For a broader view of how these gaps accumulate across the revenue cycle, see our blog on Common Causes of Pediatric Inpatient Revenue Leakage.
Pediatric Coding Cheatsheet
Use this quick pediatric coding reference to review common claim requirements before the encounter moves through final claim validation.

Quick Pre-Submission Check
- Age band correct?
- Product + admin codes present?
- Component count accurate?
- Screening fully documented?
- Modifier supported by distinct work?
- Diagnosis linked and specific?
Building a Cleaner Pediatric Claim Workflow
A clean pediatric claim is the result of alignment across documentation, coding, charge capture, payer requirements, and claim validation, not just accurate code selection.
1. Document the Encounter
Capture the services performed, clinical findings, assessment, treatment, screening results, vaccine details, and other applicable requirements.
2. Select the Appropriate Codes
Translate the documented services into the applicable CPT and ICD-10-CM codes. For organizations looking to strengthen coding accuracy at scale, Medical Coding Audit Services can help identify recurring coding and documentation gaps.
3. Capture Charges
Ensure all billable services documented in the encounter are accurately reflected in charge capture.
4. Validate the Claim
Check modifiers, diagnosis-code linkage, payer requirements, bundling considerations, telehealth requirements, and other claim edits. Pre-bill validation can help identify documentation and coding issues before they become payer-facing problems. This shift from claim-by-claim correction to upstream prevention is illustrated in AnnexMed’s Pre-Bill Documentation Controls case study, which reports a 34% reduction in reconstructive denials and describes moving documentation review earlier in the billing process.
5. Submit the Claim
Send the validated claim with the required information and supporting documentation.
6. Review Adjudication
Monitor denials, underpayments, payment variances, and payer-specific patterns.
7. Identify and Correct Upstream Gaps
Use denial and underpayment trends to identify recurring documentation, coding, workflow, or payer-configuration issues, not just to resolve individual claims.
Smarter Pediatric Billing Starts With the Right Partner
Building accurate pediatric billing workflows requires more than selecting the correct CPT code. Practices must align preventive care documentation, immunization reporting, developmental screening workflows, E/M coding, and denial prevention strategies to maintain compliance and consistent revenue performance.
AnnexMed helps providers reduce billing complexity, strengthen compliance, improve reimbursement accuracy, and streamline pediatric revenue cycle performance across every stage of care delivery.
Core Capabilities
- Pediatric CPT coding support
- Vaccine reimbursement optimization
- Modifier and denial management
- Audit-ready documentation guidance
- Telehealth compliance support
- Full-service pediatric RCM solutions
Whether managing preventive visits, vaccine billing, telehealth claims, or complex pediatric coding scenarios, having the right billing partner can significantly reduce revenue leakage while improving operational efficiency and payer compliance.
Make Pediatric Billing More Efficient
From front-end processes to claims and payment recovery, AnnexMed’s billing experts help practices streamline workflows, minimize preventable denials, and keep revenue moving.
Talk to Our Pediatric Billing ExpertsFAQs
Yes. Both may be reported on the same date when the problem-oriented E/M service is significant and separately identifiable from the preventive service. The record should include a distinct assessment and plan for the acute concern, and modifier 25 may be required.
Common reasons include missing counseling documentation, incorrect component counts, omitted vaccine product codes, missing administration codes, and incorrect use of 90460 or 90461.
Document the standardized screening tool, score or result, interpretation, identified concerns, and the follow-up plan. For example, include referrals, counseling, monitoring, or repeat-screening instructions when applicable.
Yes. CPT 90460 requires face-to-face counseling by a physician or other qualified healthcare professional for a patient through age 18. Document the counseling provided in the medical record.
Payers review modifier 25 to confirm that the separate E/M work was significant and unrelated to the usual work of the preventive service or procedure. Missing or weak documentation may result in denial or downcoding.


