Last Updated on September 28, 2026
Pathology CPT coding requires more than selecting a code that appears to match the test or specimen. Accurate billing depends on the specimen examined, service performed, number of units, professional and technical components, medical necessity, documentation, and payer-specific coverage rules.
In 2026, these requirements are especially important across surgical pathology, immunohistochemistry (IHC), flow cytometry, molecular diagnostics, next-generation sequencing (NGS), and advanced laboratory services.
For pathology groups and laboratories, the objective is not simply to submit a valid CPT code. The coded claim must accurately represent what was performed, what the documentation supports, and what the payer allows. That alignment is also the foundation of a stronger pathology revenue cycle. For organizations looking beyond individual code selection, AnnexMed’s pathology billing services cover specimen-based coding, TC/PC billing, molecular testing, claims, and denial workflows.
Table of contents
- Pathology CPT Codes at a Glance
- What Changed in Pathology Coding for 2026
- Surgical Pathology CPT Codes 88300 to 88309
- Frozen Section and Intraoperative Pathology Codes
- Flow Cytometry CPT Codes
- Molecular Pathology and NGS CPT Codes
- Why NGS Claims Get Denied Even With the Correct Code
- Outside Pathology Consultation Codes
- Common Pathology Coding Errors That Affect Reimbursement
- Pathology Claim Review Checklist
- Building a More Reliable Pathology Billing Workflow
- FAQs
Pathology CPT Codes at a Glance
The table below provides a quick reference to the major pathology coding categories covered in this guide.
| Pathology Service | Common CPT Codes or Range | Primary Billing Consideration |
|---|---|---|
|
Surgical pathology
|
88300 – 88309 | Specimen classification |
|
Intraoperative consultation
|
88329 – 88334 | Consultation method and block count |
|
Special stains
|
88312 – 88319 | Units and medical necessity |
|
Immunohistochemistry
|
88341, 88342, 88344 | Antibodies and specimens |
|
Immunofluorescence
|
88346, 88350 | Initial vs additional studies |
|
In situ hybridization
|
88365 – 88377 | Probe methodology |
|
Cytopathology
|
88142, 88175 | Preparation methodology |
|
FNA cytopathology
|
88172, 88173 | Onsite vs final interpretation |
|
Flow cytometry
|
88184 – 88189 | Markers and interpretation |
|
Molecular pathology
|
81210, 81235, 81275 and others | Coverage and diagnosis support |
|
NGS panels
|
81445, 81450, 81455 | Panel size and medical necessity |
|
Outside consultation
|
88321, 88323, 88325 | Materials reviewed |
This is not an exhaustive code list. Always validate coding against the current CPT code set, NCCI edits, CMS guidance, MAC policies, and applicable commercial payer rules.
What Changed in Pathology Coding for 2026
The 2026 laboratory code set includes additions affecting molecular diagnostics, infectious disease testing, cytogenomics, and Proprietary Laboratory Analysis codes.
Selected additions include:
- 81354: Optical genome mapping
- 81524: CNS tumor DNA methylation analysis
- 87182: Carbapenemase detection
- 87183: Carbapenem resistance gene testing
- 87494: Chlamydia and gonorrhea multiplex testing
- 87627: Joint-space pathogen panel
- 87812: SARS-CoV-2 and influenza A/B antigen testing
New PLA codes also continue to expand test-specific molecular and diagnostic coding, including prostate cancer risk assessment, liver oncology methylation analysis, and urothelial carcinoma biomarker testing.
For billing teams, adding a new code to the LIS or chargemaster is only one step. Each update should also trigger review of diagnosis requirements, test methodology, medical necessity, prior authorization, payer coverage, claim edits, and charge configuration.
Keeping Up With Pathology Coding Changes?
AnnexMed helps pathology groups and laboratories align coding updates, documentation, modifiers, and payer requirements before claims are submitted.
Explore Pathology Billing ServicesSurgical Pathology CPT Codes 88300 to 88309
Surgical pathology codes primarily depend on the specimen category and examination performed. Key codes include:
CPT 88300: Gross examination only
Confirm that microscopic examination was not performed.
CPT 88302: Lower-level pathology examination
Verify that the specimen fits the applicable specimen category.
CPT 88304: Routine surgical specimens
Confirm specimen identification and classification.
CPT 88305: Common biopsies and tissue specimens
Validate separately reportable specimens and supported units.
CPT 88307: More extensive specimens
Confirm that the specimen classification supports code selection.
CPT 88309: Highly extensive specimens
Ensure documentation supports the applicable specimen classification.
Common problems include coding according to diagnosis severity, reporting unsupported units, combining separate specimens, or relying on outdated specimen-to-code mappings.
When the same issue appears repeatedly, reviewing individual claims may not be enough. A medical coding audit can identify systemic problems in documentation, code selection, modifiers, and charge configuration.
CPT 88305 Billing Considerations
CPT 88305 is one of the most frequently reported surgical pathology codes.
Before billing, verify:
- Specimen identity
- Separately documented specimens
- Number of supported units
- Pathology report
- Professional vs technical component
- Applicable payer edits
The record should allow every billed specimen to be connected clearly with the examination and final pathology interpretation.
Frozen Section and Intraoperative Pathology Codes
Intraoperative pathology coding varies according to the consultation and examination performed.
Intraoperative Gross Consultation
CPT 88329 applies to qualifying intraoperative gross consultation. Documentation should clearly support the consultation performed.
Frozen Tissue Examination
CPT 88331 represents the initial frozen tissue block, while CPT 88332 applies to qualifying additional frozen blocks. Documentation should support the number of blocks reported.
Cytologic Evaluation
CPT 88333 represents the initial qualifying cytologic evaluation, while CPT 88334 applies to additional qualifying cytologic evaluations.
Common billing issues include missing block counts, unsupported additional units, incomplete consultation documentation, and incorrect add-on-code use.
These problems can eventually surface as bundling or coding denials. For a broader view of how such errors become payer denials, read AnnexMed’s guide to the top medical billing denials and how to prevent them.
Immunohistochemistry
IHC coding depends on the antibody study performed and whether the service represents an initial, additional, or multiplex study.
- CPT 88342: Initial single-antibody IHC study
- CPT 88341: Additional single-antibody study
- CPT 88344: Multiplex IHC study
Because several antibodies may be performed in one case, laboratories should maintain reliable antibody, specimen, and unit tracking.
Flow Cytometry CPT Codes
Flow cytometry coding includes both technical marker analysis and professional interpretation. Keeping these components separate can make code selection clearer.
Technical Marker Reporting
- CPT 88184: Initial technical marker
- CPT 88185: Each additional marker
Professional Interpretation
- CPT 88187: Interpretation of 2 to 8 markers
- CPT 88188: Interpretation of 9 to 15 markers
- CPT 88189: Interpretation of 16 or more markers
Common errors include incorrect marker counts, mixing technical and professional services, documentation that does not support the interpretation level, and duplicate reporting.
If your laboratory also handles chemistry, microbiology, and other diagnostic testing, AnnexMed’s Laboratory CPT Codes guide covers repeat testing, reference laboratory billing, and common laboratory modifiers in more detail.
Molecular Pathology and NGS CPT Codes
Molecular pathology is especially payer-sensitive because correct code selection does not automatically establish coverage.
Payers may also evaluate:
- Diagnosis
- Test indication
- Biomarker or gene
- Panel size
- Previous testing
- Medical necessity
- Prior authorization
- Test-specific coverage rules
Common Molecular Codes
- 81210: BRAF variant analysis
- 81235: EGFR variant analysis
- 81275: KRAS variant analysis
These tests frequently support cancer treatment decisions, creating a direct connection between pathology and oncology reimbursement workflows. For more on the treatment-side billing requirements, explore our oncology billing services.
NGS Panel Codes
- 81445: Qualifying solid-tumor targeted sequencing panel
- 81450: Qualifying hematolymphoid neoplasm panel
- 81455: Qualifying larger targeted sequencing panel
Why NGS Claims Get Denied Even With the Correct Code
Next-generation sequencing claims can be coded correctly and still be denied when coverage requirements are not met.
Before submission, verify:
- Correct panel selection
- Supported diagnosis
- Medical necessity
- Required prior authorization
- Test-specific payer coverage
- Performing laboratory eligibility
Missing authorization or incomplete coverage support can derail an otherwise correctly coded molecular claim. For a closer look at payer requirements, documentation, submission, and follow-up, explore our prior authorization services.
Reduce Risk in Molecular Pathology Billing
AnnexMed supports molecular pathology workflows across coding, prior authorization, documentation review, payer validation, and denial prevention.
Review Your Pathology Billing WorkflowOutside Pathology Consultation Codes
Outside pathology consultation coding depends partly on the materials received and the preparation required for the consultation.
CPT 88321: Consultation using externally prepared slides
Used when the consultation involves prepared slides received from an outside source.
CPT 88323: Consultation requiring preparation from referred tissue
Applies when additional preparation from referred tissue is required as part of the consultation.
CPT 88325: More comprehensive pathology consultation
Used for the applicable more comprehensive pathology consultation service.
Documentation should identify the originating material, preparation performed, reason for consultation, and interpretation provided.
Common Pathology Coding Errors That Affect Reimbursement
Pathology coding errors can originate at several points between specimen processing and claim submission. Common issues include:
Wrong specimen classification
Can result in incorrect CPT code selection when the billed code does not match the applicable specimen category.
Unsupported units
May lead to denials or audit exposure when additional billed units are not supported by the record.
Missing medical necessity
Can result in coverage denial even when the CPT code itself is appropriate.
Incorrect modifier 26 or TC
Can cause payment errors when the professional and technical components do not reflect how the service was performed and billed.
Unsupported additional stains
May result in denials when the documentation does not support the additional services reported.
Wrong marker count
Can affect code selection and reimbursement for flow cytometry services.
Incorrect NGS panel
May create coverage problems when the reported panel does not align with the test performed or applicable payer requirements.
Missing authorization
Can result in claim denial when prior authorization is required.
Outdated coding library
Can lead to incorrect claim submission when current coding requirements are not reflected in billing systems.
Unbundled services
May trigger NCCI edits when services are reported separately contrary to applicable bundling rules.
Recurring denials should be traced back to the workflow that created them. AnnexMed’s guide to common medical billing denials explains how coding, documentation, authorization, and payer-rule problems become downstream denials.
When claims are already denied, denial management services can help resolve them while identifying upstream causes that should be prevented.Pathology Modifiers and When They Apply
| Modifier | Purpose |
|---|---|
| 26 |
Professional Component
|
| TC |
Technical Component
|
| 90 |
Reference Laboratory
|
| 91 |
Medically necessary repeat laboratory testing
|
| 59 |
Distinct procedural service
|
| 92 |
Qualifying alternative laboratory platform
|
Modifier 26 vs TC
- Modifier 26 identifies the professional component, such as qualifying pathologist interpretation.
- Modifier TC identifies the technical component where applicable.
If the same eligible entity performs and bills both portions and payer rules permit global billing, neither modifier may be required.
Repeated modifier problems often indicate a workflow issue rather than an isolated coder error. Our Coding and Documentation Analytics can help identify code-utilization, modifier, and documentation patterns across larger claim volumes.
Pathology Claim Review Checklist
Before submission, verify:
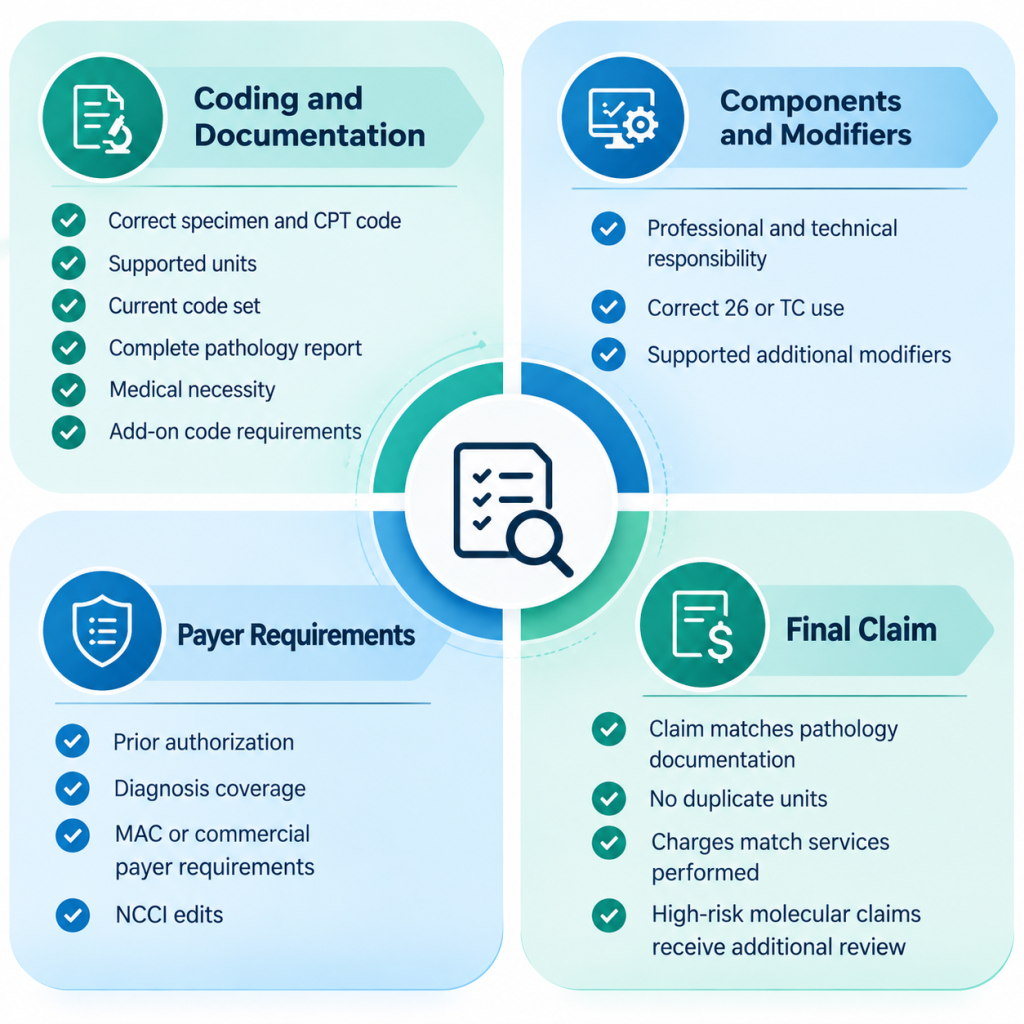
Repeated specimen classification or unit errors should be reviewed at the workflow level rather than corrected claim by claim.
Organizations that repeatedly find the same problems during pre-bill review may benefit from a structured medical coding audit rather than continuing to correct claims individually.
Building a More Reliable Pathology Billing Workflow
Pathology reimbursement depends on keeping coding, documentation, payer rules, and payment workflows aligned from specimen to final reimbursement.
AnnexMed supports pathology groups, diagnostic laboratories, and hospital-based departments across the full billing cycle, with focus on:
- Specimen-based coding accuracy for surgical, molecular, and ancillary pathology services
- TC/PC and modifier validation to support correct component billing
- Prior authorization and payer alignment for high-complexity and molecular testing
- Denial, A/R, and payment review to identify recurring reimbursement gaps
The goal is not only to correct rejected claims, but to identify where the issue originates and prevent the same problem from continuing across future claims.
For organizations managing complex pathology volumes, AnnexMed brings coding, billing, denial prevention, and reimbursement review into one connected workflow.
Strengthen Pathology Billing From Specimen to Payment
AnnexMed helps pathology groups, laboratories, and hospital departments improve coding accuracy, claim quality, denial prevention, and reimbursement workflows.
Talk to Our Pathology Billing ExpertFAQs
Surgical pathology commonly uses CPT codes 88300–88309. The appropriate code depends primarily on the applicable specimen category and examination performed.
Both are surgical pathology codes, but they apply to different qualifying specimen categories. Code selection should follow the current CPT specimen classification.
Modifier 26 identifies the professional component of an eligible pathology service, while TC identifies the technical component.
Frequent causes include coverage mismatches, unsupported medical necessity, incorrect panel selection, missing prior authorization, and incomplete documentation.
Codes 88184 and 88185 address technical marker reporting, while 88187–88189 differentiate professional interpretation according to marker count.
Yes. Component billing errors, contract differences, payer edits, unit reductions, and incorrect adjustments can create payment variances even when the claim was paid.